Contents
What must be retained from 2018–2025 evidence
Three advances have transformed the management of root resorption: (1) The Patel 2018 3D classification (height · circumference · canal contact) gives a reproducible, prognosis-linked staging for ECR using CBCT — largely replacing the Heithersay H1–H4 system for lesion planning. (2) Mavridou et al. 2022 published a comprehensive decision algorithm integrating CBCT stage, restorability, and treatment modality. (3) Biodentine has become the material of first choice for ECR restoration (biocompatible, seals the canal wall, allows immediate provisionalization) and for internal resorption perforation repair. TCA 90 % as a chemical adjunct to ECR surgical management remains validated. Post-traumatic EIRR (type 2 and 3 after avulsion/luxation) remains an absolute emergency — each hour without replantation worsens prognosis.
Definition, epidemiology and classification
Root resorption is the pathological destruction of dental hard tissue (cementum, dentine, and sometimes enamel) by clastic cells (odontoclasts / osteoclasts). It can originate from within the root canal system (internal resorption) or from outside the root surface (external resorption). All forms are pathological — physiological resorption does not occur in permanent teeth.
Main classification — by location
Internal resorption: initiated from the pulp canal by activated clasts following chronic pulpitis. Enlarges the canal from within. External resorption: initiated from the periodontal ligament, cementum surface, or alveolar bone. Four main subtypes: cervical (ECR), inflammatory (EIRR), replacement (ankylosis), orthodontically induced (OIIRR).
Andreasen classification (1985)
Still a valid teaching reference. Surface resorption: self-limiting, reversible (cemental repair). Inflammatory resorption: progressive, driven by bacterial infection of the dentinal tubules. Replacement resorption: ankylosis — bone replaces the root. Cervical resorption: invasive — begins below the gingival epithelial attachment. Each subtype has different aetiology, prognosis, and management.
Triggering factors
Trauma: avulsion, luxation, concussion. Orthodontic treatment: heavy and prolonged forces. Internal bleaching: hydrogen peroxide diffusion through dentinal tubules. Periodontal disease: chronic inflammation. Impacted teeth: dentigerous pressure. Systemic: hyperparathyroidism, Paget's disease, Gaucher's disease (uncommon).
Epidemiology — key figures
ECR prevalence: 1.7–7 % of patients (Cohen et al.). OIIRR: 1–5 % of orthodontic patients show moderate to severe resorption. EIRR: affects up to 74 % of avulsed teeth if replantation is delayed >60 min (dry storage). Internal resorption: rare (<1 % of endodontic cases), but significantly underdiagnosed before pulp is exposed.
External cervical resorption (ECR)
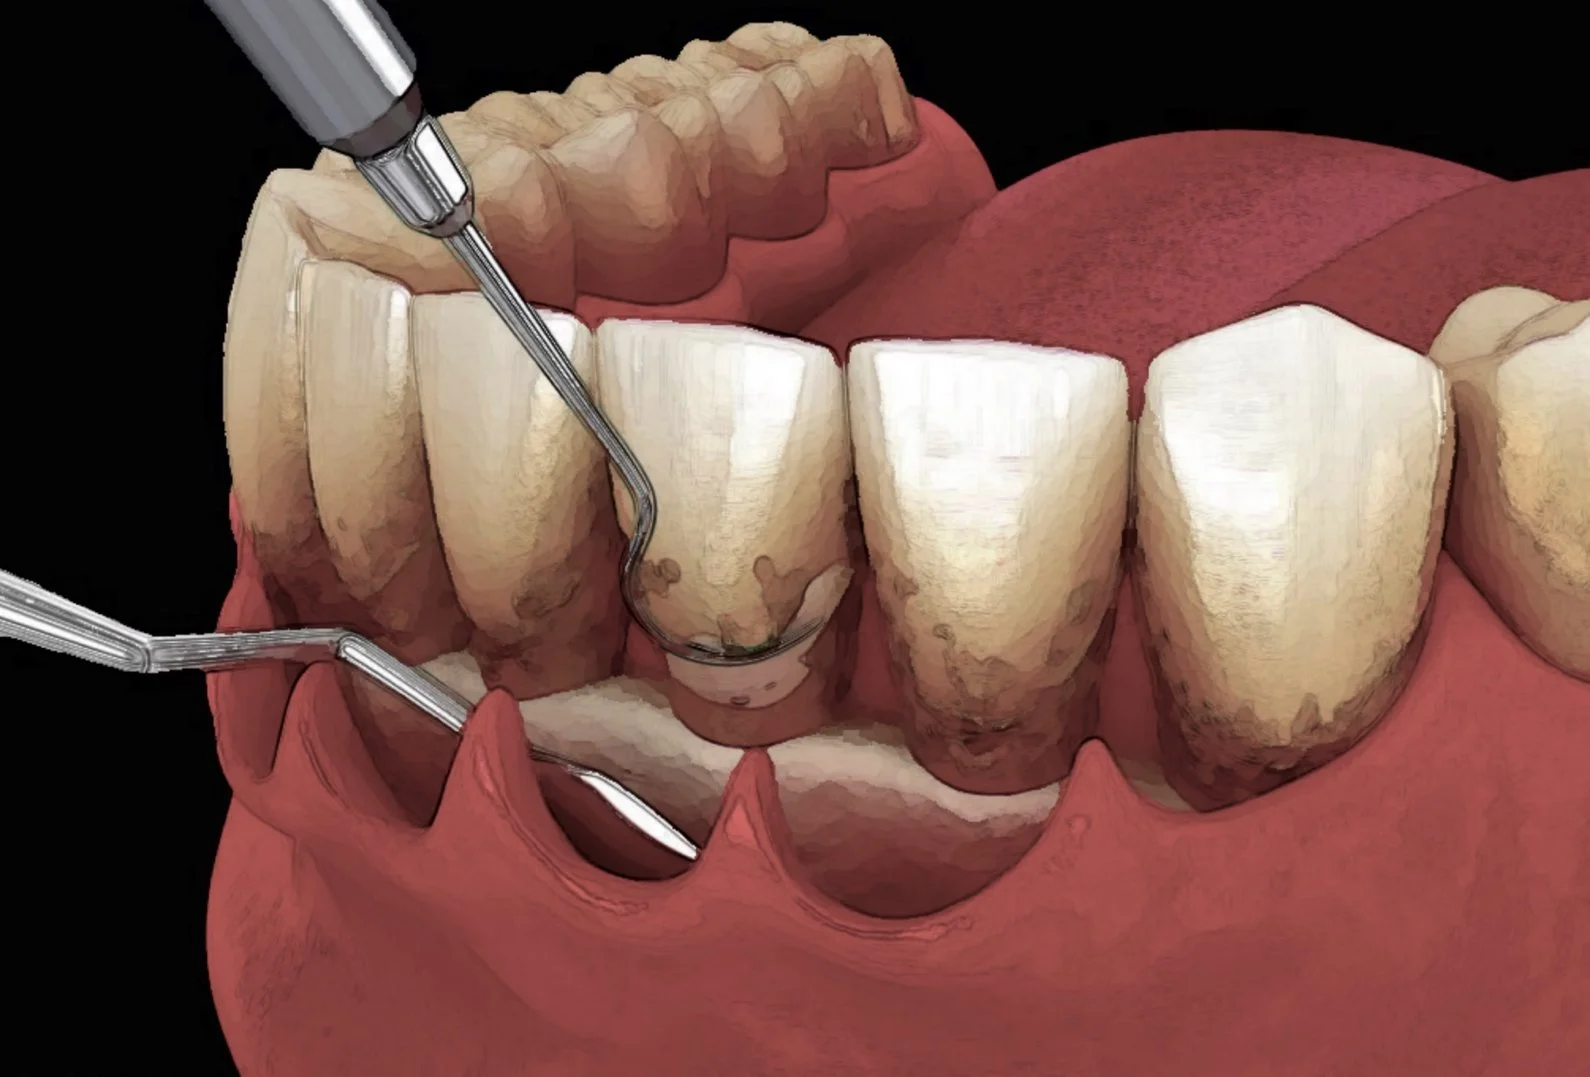
External cervical resorption (ECR), also called invasive cervical resorption (ICR) or peripheral inflammatory root resorption (PIRR), is the most clinically complex form of external resorption. It begins below the epithelial attachment of the gingiva (at the level of the cemental-enamel junction or just below), and invades the root progressively while the pulp typically remains vital until late stages.
Pathogenesis
Clastic cells access the root surface at the level of the cemento-enamel junction (CEJ) following disruption of the protective cementum layer (trauma, orthodontic movements, periodontal surgery, bleaching). The fibrous vascular tissue infiltrates the root, progressively destroying cementum and dentine in a lacunar pattern. The pulp is protected by a pre-dentine layer until very advanced stages.
Clinical presentation
Often asymptomatic for years — discovered incidentally on a routine radiograph. The tooth is vital (positive pulp test in most cases until late stages). The gingival tissue over the resorptive lesion may appear pink or reddish (pink discolouration through the enamel — "pink spot"). No spontaneous pain unless superinfection occurs.
Heithersay classification (1999)
Class H1: small, confined to coronal dentine. Class H2: deeper into dentine — not reaching the canal. Class H3: extends to the coronal or middle third of the root — not penetrating the canal. Class H4: massive — reaches the apical third or penetrates the canal. H1–H2: good prognosis. H3: guarded. H4: poor, often unrestorable.
Differential diagnosis — ECR vs caries vs IRR
vs caries: ECR lesion is sub-epithelial, does not start at the enamel surface, is harder to probe, and the tooth is vital. vs internal resorption (IRR): ECR is eccentric (off-centre) on the periapical radiograph; IRR is central (the lesion moves with angulation changes). CBCT is decisive in ambiguous cases.
ECR can remain radiographically undetected until the lesion is large (2D radiographs underestimate ECR volume significantly). A "stable-looking" lesion on successive periapical radiographs may actually be progressing in the buccal/lingual dimension invisible on 2D imaging. Any suspected ECR should be assessed with CBCT before deciding watchful waiting — asymptomatic does not mean non-progressive.
Internal root resorption (IRR)
Pathogenesis and aetiology
IRR results from the activation of clasts within the root canal system following chronic irreversible pulpitis — often secondary to caries, trauma, or restorative procedures. Clastic cells attach to the canal walls and resorb dentine centrifugally, progressively enlarging the canal lumen. A vital periphery of residual pulp tissue is required for progression — hence, IRR stops once the pulp becomes fully necrotic.
Radiographic and clinical features
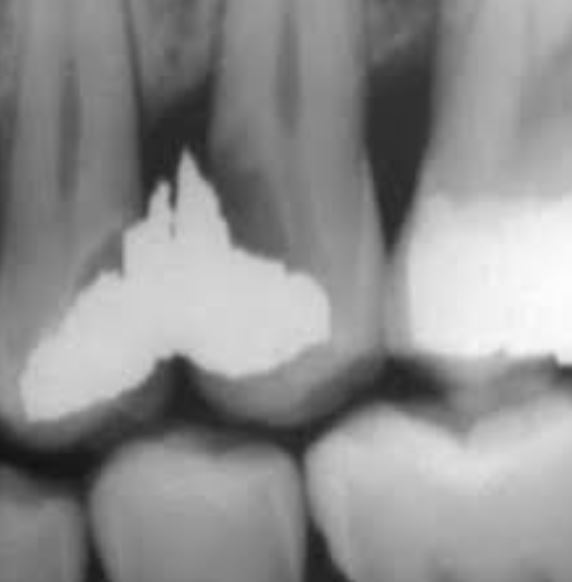
Classic radiographic appearance: oval or round radiolucent enlargement of the canal lumen, well-defined and smooth margins, centred within the root (unlike ECR which is eccentric). The lesion moves with the tooth on angulated views. Pulp test: often positive (partially vital pulp). Tooth usually asymptomatic until perforation. "Pink spot" on the crown if the lesion reaches the coronal dentine.
Complications — perforation
IRR can perforate the root laterally if untreated, creating a communication between the canal and the periodontal space. Signs: sudden pain, sinus tract, pocket probe reaching the perforation level. Prognosis depends on: location (cervical perforations = poor), size of perforation, time elapsed before treatment. Biodentine or MTA is the material of choice for perforation repair.
Treatment
Non-perforating IRR: standard root canal treatment — complete pulp extirpation stops resorption. The irregular canal walls require copious NaOCl irrigation (5.25 %) and warm obturation (thermoplastic gutta-percha or Biodentine). Perforating IRR: MTA or Biodentine perforation repair via orthograde or surgical (flap) approach. Prognosis: good to excellent if treated before perforation; guarded after perforation depending on size and site.
External inflammatory root resorption (EIRR)
EIRR is the most urgent form of root resorption. It develops on the external root surface, driven by bacterial infection of the dentinal tubules communicating with the periodontium. It is most commonly encountered after dental trauma (avulsion, extrusive/lateral luxation) but can also occur in chronic periapical periodontitis. Without treatment, EIRR can destroy an entire root within weeks.
Type 1 — Transient surface resorption
Self-limiting. Small lacunar defects on the root surface. Seen in minor trauma (subluxation, concussion). Cemental repair occurs spontaneously. No treatment required. Radiographically: small irregular surface defects without progressive widening at 3 months.
Type 2 — Inflammatory EIRR (progressive)
Driven by bacterial infection of necrotic pulp. Progressive — destroys the root rapidly. Radiograph: periapical radiolucency + lateral root surface destruction. Emergency: root canal treatment eliminates the bacterial source. Each day without treatment = irreversible root volume loss.
Type 3 — Ankylosis / replacement resorption
Occurs when the PDL is necrotic (dry avulsion >60 min). The root is progressively replaced by bone (endosteal resorption). On percussion: metallic sound (ankylosed tooth). No treatment arrests this — see Section 5 for management strategy.
After dental avulsion, EIRR type 2 can begin within 7–10 days of replantation if the pulp is not treated. The standard protocol: root canal treatment 7–10 days post-replantation (before the inflamed PDL is replaced by irreversible resorption). For avulsion with dry extra-oral time >60 min: immediate root canal treatment prior to replantation (dead PDL cells cannot be saved — focus on eliminating the infection source). Delayed treatment by even 3–4 weeks can result in complete root destruction within 3 months.
External replacement resorption — ankylosis
Replacement resorption (ankylosis) occurs when necrotic periodontal ligament cells are replaced by bone directly apposed to the root surface. The root is gradually substituted by bone in an endosteal resorption process. There is no effective treatment to arrest the process — management is directed at slowing progression and planning future options.
Diagnosis
Percussion: high-pitched metallic sound (diagnostic — sensitivity ~80 %). Radiograph: loss of PDL space, continuity between alveolar bone and root, progressive root volume reduction. CBCT: quantifies the extent of ankylosis before deciding on treatment strategy. Infra-occlusion: in children — ankylosed tooth does not erupt with alveolar growth, progressively submerging below the occlusal plane.
Impact on growth — children and adolescents
Ankylosis in children causes progressive infra-occlusion as the alveolar bone grows around the submerged tooth. Clinical consequences: occlusal collapse, tipping of adjacent teeth, reduced alveolar height. An ankylosed tooth in a growing child is an orthopedic problem requiring proactive management, not just monitoring.
Decoronation — Malmgren technique
Standard of care for ankylosed teeth in growing patients (Malmgren et al.). Removes the clinical crown, leaving the ankylosed root in place to preserve alveolar bone volume. The root resorbs slowly over years and is replaced by bone. Advantages: alveolar bone is maintained for future implant placement. Timing: when infra-occlusion exceeds 1 mm or inhibits adjacent tooth eruption.
Options in adults
If ankylosis is localised and cosmetically acceptable: monitoring. If progressive with bone loss: extraction + immediate bone grafting (ARP protocol) for future implant. Implant placement deferred until growth is complete (girls ≥17, boys ≥18–20 years — cephalometric confirmation). In adults: surgical luxation to disrupt ankylosis is possible but rarely successful long-term.
Orthodontically induced inflammatory root resorption (OIIRR)
Definition and risk factors
OIIRR is a common complication of fixed orthodontic treatment — apical root resorption caused by mechanical forces applied to teeth. Risk factors: intrusive movements, heavy continuous forces, long treatment duration (>2 years), upper central and lateral incisors (most vulnerable), pre-existing root morphology anomalies (pipette-shaped, blunt apices), genetic predisposition (IL-1β polymorphisms).
Severity grading
Grade 1: blunted root tip — no clinical significance. Grade 2: root shortening <2 mm — monitored. Grade 3: shortening 2–4 mm — treatment modification required. Grade 4: root length reduction >4 mm or >1/3 of original length — poor prognosis, consider orthodontic treatment pause.
Clinical management
Periapical radiographs at 6-month intervals during active treatment for at-risk patients. If Grade 3 detected: 3-month rest period (minimal forces) — cemental repair may occur. If Grade 4: discuss treatment interruption with the orthodontist. Post-treatment: annual periapical follow-up for 2–3 years. Avoid implants on OIIRR-affected teeth with root length <9 mm (inadequate bone support).
Bleaching-associated external cervical resorption
Internal bleaching of non-vital teeth with hydrogen peroxide (H₂O₂) is a well-documented risk factor for external cervical resorption. The diffusion of H₂O₂ through dentinal tubules to the external root surface appears to trigger clastic activity at the cemento-enamel junction. The risk is significantly reduced by the placement of a protective cervical barrier before bleaching.
Mechanism — H₂O₂ diffusion
H₂O₂ (35 % thermocatalytic bleaching — now abandoned, or 30–35 % walking bleach) diffuses through dentinal tubules to the external cementum surface. It disrupts the protective cementum layer at the CEJ, allowing PDL clastic cells to access the dentine. The risk is higher at alkaline pH and with higher peroxide concentrations. The thermocatalytic technique is abandoned for this reason.
Prevention — cervical barrier
Mandatory: cervical barrier of Biodentine or glass-ionomer, 2–3 mm coronal to the CEJ, before any internal bleaching. The barrier physically prevents H₂O₂ from reaching the root surface. A Cavit or Fuji IX barrier placed only at the CEJ level is insufficient — it must extend 2–3 mm above. All protocols now use Biodentine as the barrier material of choice (biocompatible, seals tubules).
Walking bleach — safer protocol
Sodium perborate + water (NOT + H₂O₂) — recommended by Frank et al. (J Endod 2022). Efficacy equivalent to perborate + H₂O₂ but with lower ECR risk. Protocol: sodium perborate paste placed in the pulp chamber, sealed for 1–2 weeks between visits. After bleaching: wait 2 weeks before resin composite placement (residual peroxide inhibits polymerisation).
1. Root canal treatment must be complete and radiographically confirmed at least 3 months prior. 2. Cervical barrier: Biodentine 2–3 mm coronal to the CEJ — placed BEFORE the bleaching agent. 3. Use sodium perborate + water (NOT perborate + H₂O₂) — lower ECR risk, equivalent efficacy. 4. Limit to 3–4 bleaching sessions maximum. 5. Inform the patient of the ECR risk and schedule radiographic follow-up at 6 months, 1 year, and 2 years.
Patel 2018 three-dimensional CBCT classification
The Patel 2018 three-dimensional classification of ECR (published in the International Endodontic Journal) was developed to overcome the limitations of 2D Heithersay grading for treatment planning. It uses CBCT measurements in three dimensions and provides a more accurate, reproducible staging that directly guides surgical approach and prognosis.
| Dimension | Stage 1 | Stage 2 | Stage 3 | Stage 4 |
|---|---|---|---|---|
| Height (corono-apical extent) | Confined to coronal third only | Extends to middle third | Extends to apical third | Extends to the full length of the root |
| Circumference (% of root circumference) | <90° | 90°–180° | 180°–270° | >270° (wraps around root) |
| Canal contact | Suffix A: no canal contact · Suffix B: canal contact (lesion reaches the root canal system) | |||
Stage 1A / 2A — Good prognosis
Small, contained lesions not reaching the canal. Accessible via conventional surgical approach (flap + curettage + Biodentine/composite restoration). 5-year survival >85 % in published series. Root canal treatment not mandatory if pulp remains vital and lesion doesn't contact the canal.
Stage 2B / 3A — Guarded prognosis
Larger lesions ± canal contact. Root canal treatment likely required (even if pulp currently vital — canal integrity is compromised). More complex surgical access (possibly combined orthograde + surgical approach). Prognosis dependent on remaining root dentine thickness after curettage.
Stage 3B / 4 — Poor prognosis
Extensive circumferential lesions and/or reaching apical third with canal contact. Root wall integrity likely compromised. Often unrestorable — extraction with ARP socket preservation recommended. If the patient strongly wishes to preserve the tooth: specialist referral — attempt repair with MTA or Biodentine, accepting a guarded prognosis.
Diagnosis — clinical, radiological and CBCT
| Type | Vitality test | 2D radiograph | CBCT contribution | Key clinical sign |
|---|---|---|---|---|
| ECR | Positive (until late) | Eccentric radiolucency near CEJ — lesion moves with angulation change | Circumference, height, canal contact — essential for staging | Pink spot on crown (sometimes) |
| IRR | Positive | Central oval/round canal enlargement — symmetrical, moves with the tooth | Confirms centred position — rules out ECR | Asymptomatic until perforation |
| EIRR type 2 | Negative (necrosis) | Periapical lucency + lateral root destruction — "moth-eaten" appearance | Quantifies root volume remaining | Trauma history, recent replantation |
| Ankylosis | Normal or negative | Absent PDL space, root/bone continuity | Extent of ankylosis — infra-occlusion measurement | Metallic percussion sound |
| OIIRR | Positive | Blunted or shortened apices, often upper incisors | Accurate 3D root length measurement | Active orthodontic treatment |
The paralleling technique for ECR — critical
For suspected ECR: take two periapical radiographs with different horizontal angulations (horizontal parallax). If the lesion moves relative to the root with angulation change: external (ECR). If it stays centred with the canal regardless of angulation: internal (IRR). This Clark's SLOB rule (Same Lingual, Opposite Buccal) is the decisive 2D differential before CBCT.
CBCT indications in resorption
CBCT is indicated for: any ECR H2 or above before treatment planning; EIRR with uncertain remaining root volume; suspected IRR with perforation; complex retreatment cases. Not mandatory for: small ECR H1 clearly accessible via 2D; OIIRR monitoring (serial periapicals sufficient); IRR without perforation on 2D.
Treatment principles — ECR
Treatment — EIRR, ankylosis and OIIRR
| Type | Treatment | Material / drug | Prognosis | Follow-up |
|---|---|---|---|---|
| EIRR type 1 (surface) | None — self-limiting | — | Excellent | PA radiograph at 6 months |
| EIRR type 2 (inflammatory) | Emergency root canal treatment + Ca(OH)₂ dressing | Ca(OH)₂ paste, replace every 3 months | Dependent on root volume at presentation | PA at 3, 6, 12 months |
| EIRR type 3 (ankylosis) | Decoronation (child) or extraction + ARP (adult) | Malmgren decoronation | Poor — root progressively replaced by bone | Annual CBCT in growing patients |
| Ankylosis (isolated) | Surgical luxation (limited success) or extraction + ARP + future implant | MTA if IRR associated | Poor for tooth retention | 6-monthly for infra-occlusion monitoring |
| OIIRR Grade 3–4 | Orthodontic treatment pause + re-evaluation | — | Dependent on root length remaining | PA at 3 months, then 6-monthly |
Mavridou 2022 decision algorithm
Mavridou et al. (2022) proposed a comprehensive decision algorithm integrating clinical findings, CBCT staging, and evidence-based treatment options. It is the most complete current reference for ECR management decisions. The algorithm proceeds in three sequential steps.
Step 1 — Is the tooth restorable?
CBCT evaluation of residual dentine walls. If <1.5 mm remaining after curettage: unrestorable → extraction + ARP. If ≥1.5 mm: proceed to Step 2. Key: a tooth that appears "saveable" on 2D may be unrestorable on CBCT — always CBCT stage before committing to surgical repair.
Step 2 — Is the canal involved?
Patel suffix A vs B. Suffix A (no canal contact): surgical ECR repair alone. Suffix B (canal contact): root canal treatment mandatory (before or during surgery). The pulp may still be vital in suffix B — root canal treatment is required regardless, because the canal integrity has been breached.
Step 3 — What surgical access?
Supracrestal lesion: conventional flap access. Subcrestal: orthodontic extrusion + delayed surgery, or surgical crown lengthening before repair. Circumferential (>180°): consider if repair is technically feasible or if extraction with ARP is a better long-term option for the patient's overall treatment plan.
Materials, evidence and Algerian context
Biodentine — first-choice material for ECR repair
Tricalcium silicate-based cement (Septodont). Biocompatible, induces cementum-like hard tissue, seals dentinal tubules, allows immediate loading in 12 minutes. Key advantage over MTA: can be used as a definitive material for small cavities or as a sub-base replaced by composite at 12 weeks (after complete setting). Available in Algeria (Extradent, MDI — Dentex 2026).
MTA (Mineral Trioxide Aggregate)
Reference material for perforation repair (IRR perforation, ECR with canal contact). Long clinical track record. Long setting time (24–48 h) — patient must avoid biting on the tooth. ProRoot MTA (Dentsply Sirona) is the most documented. Available in Algeria (Extradent, MDI — distributed as Biodentine and MTA at Dentex 2026 stands B08/C03 and B11).
TCA 90 % — ECR chemical adjunct
Trichloroacetic acid 90 % — used intra-surgically to chemically devitalise resorptive fibrovascular tissue before curettage and restoration. Heithersay protocol: 1–2 min application. Reduces recurrence vs curettage alone (Heithersay 1999 series). Preparation: pharmaceutical compounding — available from pharmacies or dental suppliers.