
Why maintenance determines implant survival
Modern implant dentistry reports survival rates above 95% at ten years in well-monitored cohorts, a figure that has durably established — in the minds of many clinicians and their patients alike — the notion of a definitive, almost indestructible solution. That perception is misleading. Implant survival is not synonymous with implant health: an implant can remain osseointegrated and functional while harbouring a chronic progressive inflammation that silently destroys its bony support. Epidemiological data compiled by Derks and Tomasi estimate the prevalence of peri-implant mucositis at approximately 43% of implant patients and that of peri-implantitis at approximately 22%, with substantial heterogeneity attributable to the case definitions applied. In other words, close to one implant patient in five will develop a genuinely destructive disease around their implants.
The variable that most clearly separates patients who develop peri-implantitis from those who do not is neither the implant brand, nor its surface characteristics, nor the surgical technique: it is the presence — or absence — of a structured maintenance programme. The study by Costa and colleagues showed that in patients with pre-existing mucositis, the five-year incidence of peri-implantitis reached 43.9% in the absence of maintenance, against 18% in patients under regular supportive care. Supportive peri-implant therapy is therefore not an optional comfort service: it is the second half of implant treatment, the half that determines whether the patient's surgical and prosthetic investment lasts ten years or thirty.
Placing an implant without a formalised maintenance plan constitutes incomplete treatment. Pre-implant informed consent should explicitly state that follow-up is mandatory, along with its expected frequency and cost, on the same footing as surgical risks.
A second paradigm shift deserves mention at the outset. Classical teaching long presented peri-implantitis as simply "periodontitis around an implant", treatable by direct transposition of periodontal protocols. Current evidence imposes a more nuanced reading: the peri-implantitis lesion progresses faster than its periodontal counterpart, extends apically in a characteristic circumferential pattern, displays a more extensive inflammatory infiltrate, and responds distinctly less well to non-surgical therapy. This difference in biological behaviour — detailed in the DentoLink article on the classification of periodontal and peri-implant diseases — justifies a dedicated diagnostic and therapeutic approach, which is the subject of the present article.
Definitions and diagnosis: health, mucositis, peri-implantitis
2.1The 2017 World Workshop classification
The 2017 World Workshop (joint AAP/EFP consensus, report by Berglundh and colleagues) equipped the discipline with operational case definitions that should structure every examination. Peri-implant health is defined by the absence of visual signs of inflammation, the absence of bleeding on gentle probing, and the absence of bone loss beyond initial remodelling. A crucial and frequently misunderstood point: peri-implant health is not defined by a threshold probing depth. An implant placed subcrestally or submerged beneath thick mucosa may exhibit perfectly healthy depths of 5 mm; it is comparison with the patient's own baseline values that carries meaning, not an absolute figure.
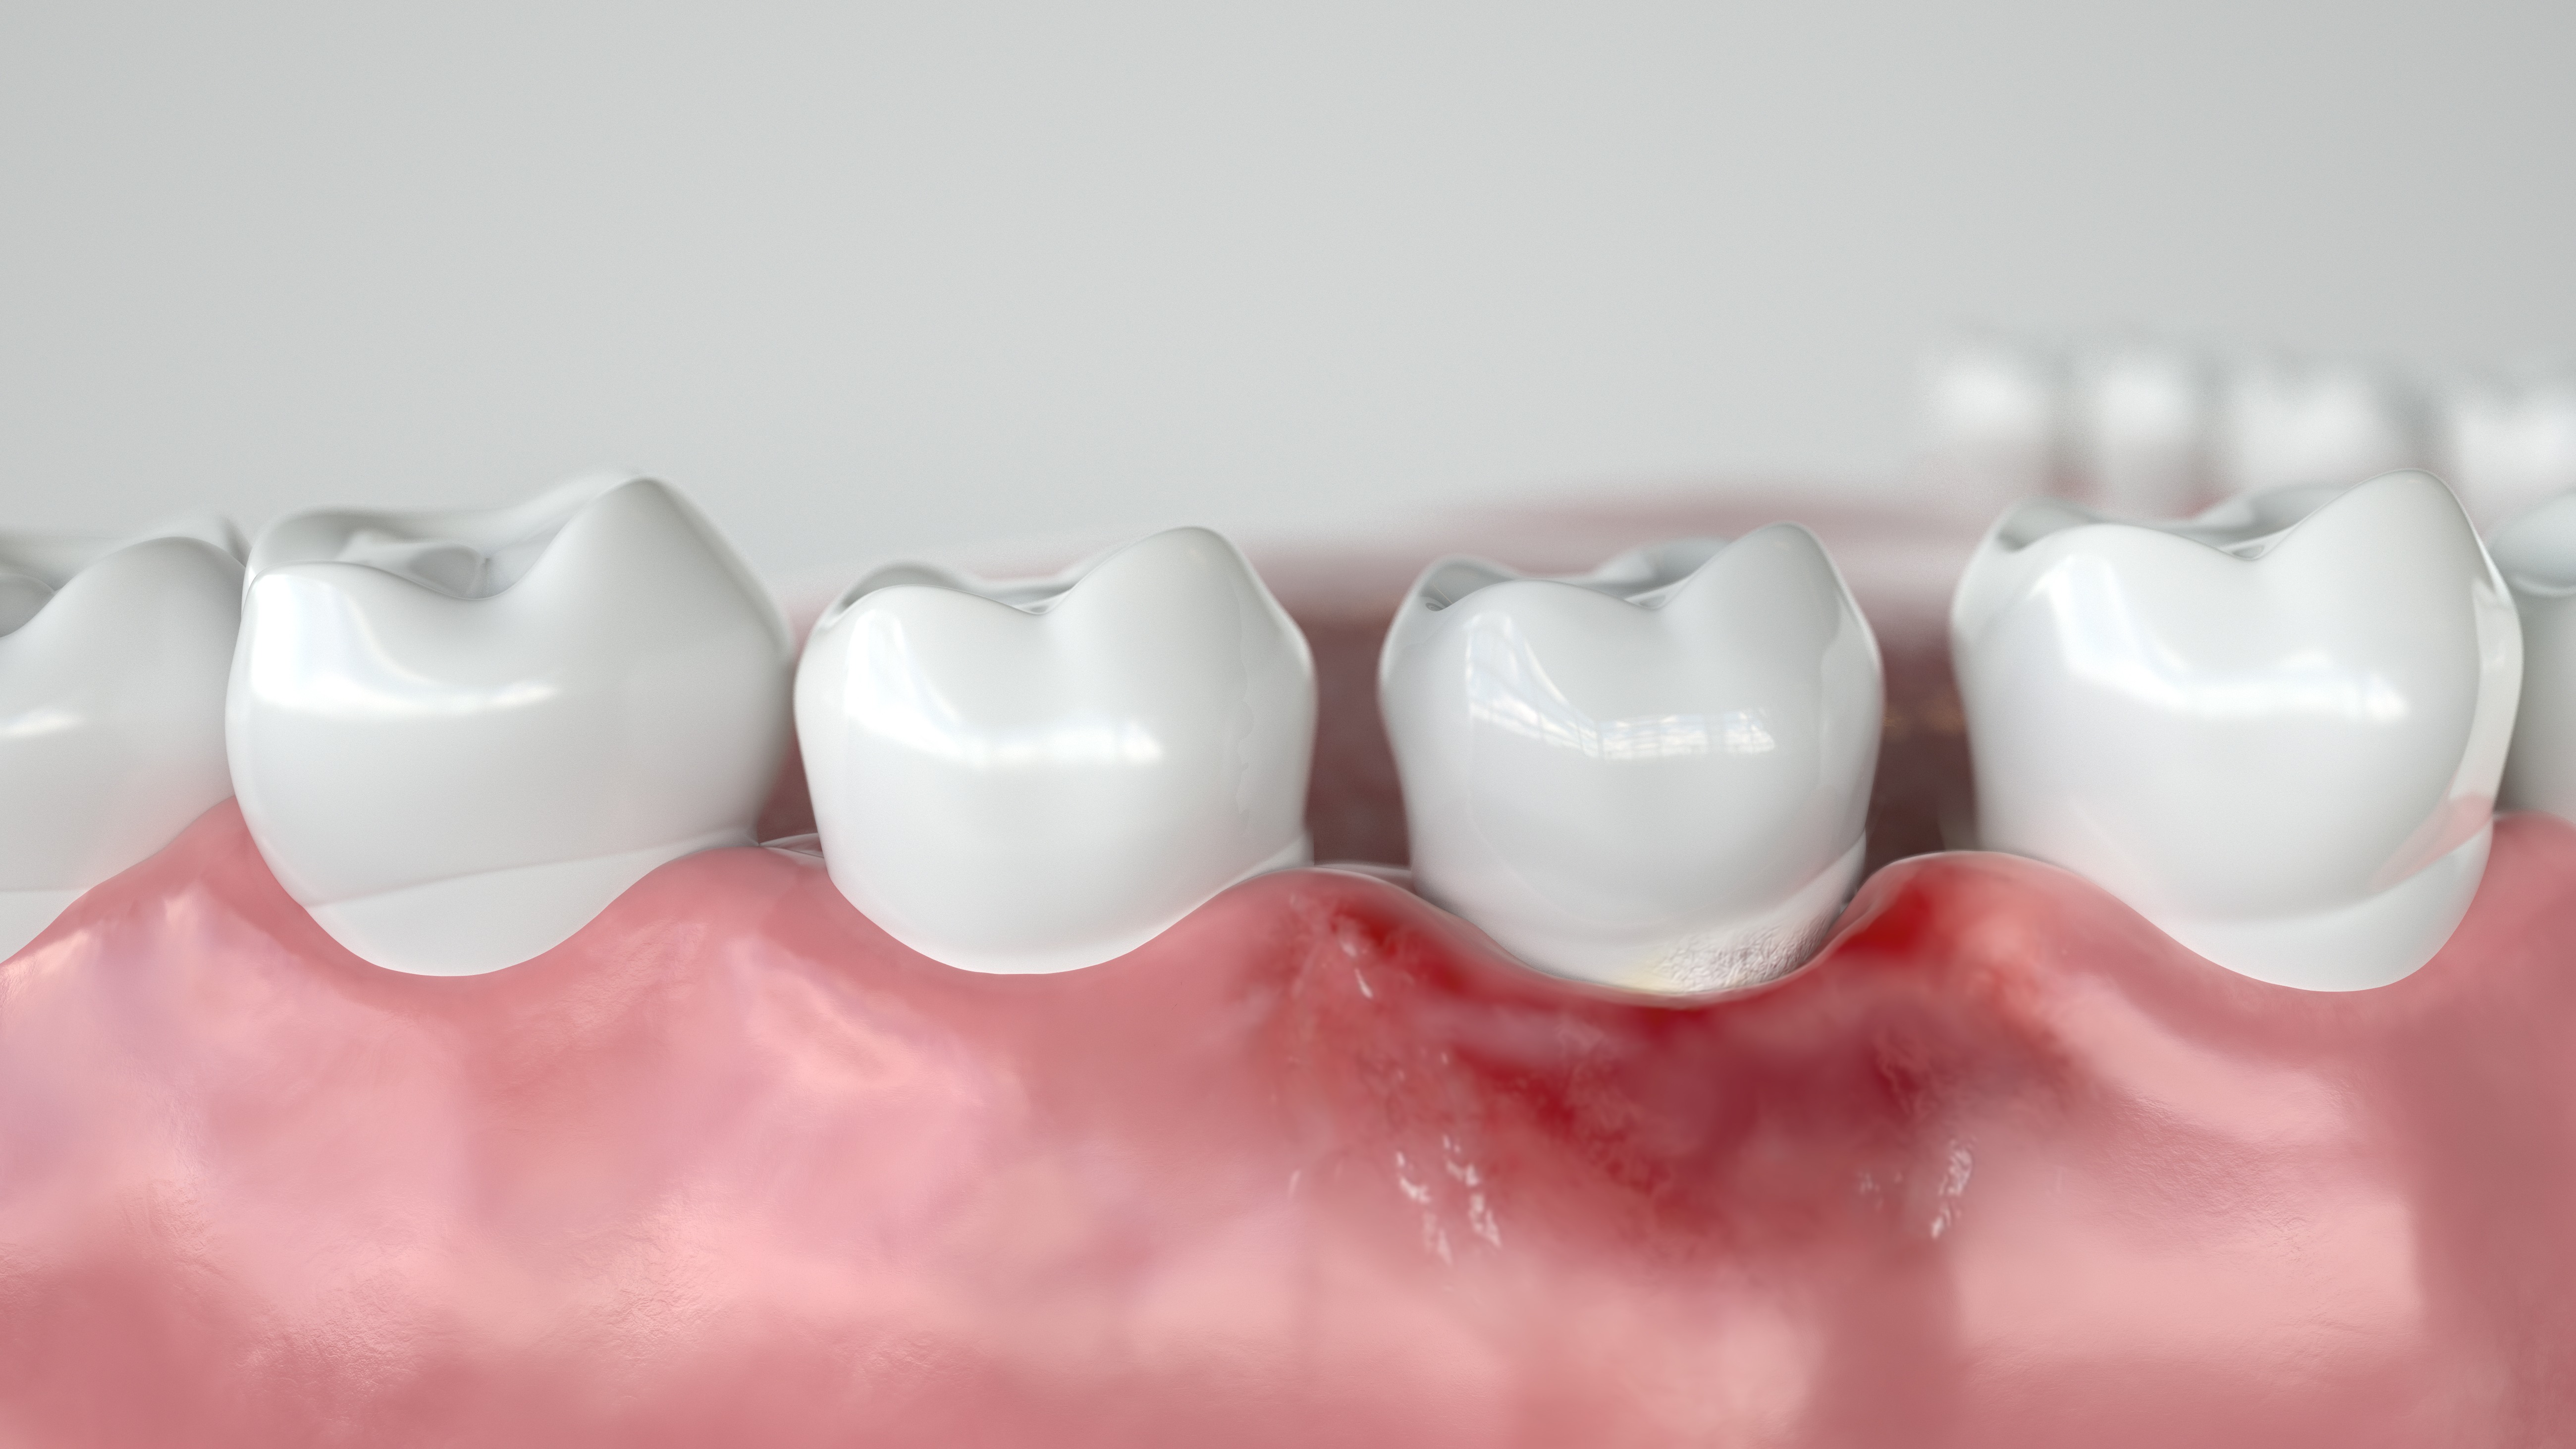
Peri-implant mucositis corresponds to soft-tissue inflammation — bleeding on probing, possibly with redness, oedema or suppuration — without bone loss beyond initial remodelling. It is reversible, biofilm-induced, and constitutes the obligatory precursor of peri-implantitis, exactly as gingivitis precedes periodontitis. Peri-implantitis combines soft-tissue inflammation with radiographically documented progressive bone loss. In the absence of baseline radiographs, the consensus proposes fallback criteria: bleeding or suppuration on probing, probing depth of 6 mm or greater, and a bone level situated 3 mm or more apical to the most coronal portion of the intraosseous part of the implant.
| Entity | Bleeding / suppuration | Bone loss | Reversibility |
|---|---|---|---|
| Peri-implant health | Absent | None beyond remodelling | — |
| Mucositis | Present | None beyond remodelling | Reversible with biofilm control |
| Peri-implantitis | Present | Progressive, radiographically documented | Irreversible; stabilisation achievable |
2.2The importance of the baseline reference
The entire diagnostic logic rests on comparison with a reference state. The periapical radiograph taken at delivery of the definitive prosthesis — not at surgical placement of the implant — constitutes the baseline document: it captures the bone level after initial physiological remodelling and allows a clinician, years later, to distinguish pathological loss from long-settled remodelling. Likewise, probing depths recorded at loading serve as individual reference values. An implant record without a baseline radiograph or baseline probing deprives the clinician of any landmark and turns every subsequent decision into a gamble. This documentary requirement converges with the medico-legal principles detailed in the DentoLink article on patient records and traceability.
Never diagnose peri-implantitis on probing depth alone. A stable 6 mm reading without bleeding, around a deeply placed implant, is compatible with health. Conversely, a site that has moved from 3 to 5 mm with bleeding signals deterioration, even though the absolute value appears unremarkable.
The peri-implant examination in practice
3.1Probing: indispensable and harmless
A reluctance persists among some clinicians to probe implants, for fear of disrupting the epithelial attachment or scratching the surface. That fear is unfounded: gentle probing at a force of roughly 0.25 N has no lasting consequence for the peri-implant tissues, whose seal re-forms within a few days. Systematic probing at four to six sites per implant, at every maintenance visit, is the only method that detects bleeding — the cardinal sign of mucositis — and tracks changes in depth over time. A conventional metal periodontal probe is entirely suitable; plastic probes, historically recommended, have never demonstrated clinical benefit, and their flexibility may in fact distort measurement around superstructures with pronounced emergence profiles.
3.2Other clinical parameters
The examination then looks for suppuration, either spontaneous or elicited by digital buccal pressure, which points strongly toward peri-implantitis. Mobility is not an early sign: a mobile implant is an implant that has lost osseointegration, a terminal situation mandating removal. It is nonetheless essential to distinguish implant mobility from superstructure mobility — a loosened prosthetic screw mimics implant mobility and is corrected simply. Finally, the examination assesses hygiene accessibility: an over-contoured emergence profile, closed embrasures, or a non-retrievable full-arch bridge render plaque control illusory and constitute prosthetic risk factors in their own right, developed in section 7.
3.3Imaging
The periapical radiograph taken with a beam-aiming device, in reproducible orthogonal projection, remains the reference examination for monitoring proximal bone level. It is indicated when peri-implantitis is suspected, and again to document stability after treatment — not as a routine annual film in the healthy patient, where clinical examination suffices as long as no warning sign appears. CBCT has no place in screening: metal artefacts degrade immediate peri-implant reading. It is justified solely in pre-surgical planning of peri-implantitis treatment, when the three-dimensional morphology of the defect — circumferential, buccal dehiscence, crater — determines the choice between reconstructive and resective approaches.
The maintenance visit: protocol and instrumentation
4.1Sequence of a typical visit
Medical and behavioural update. Refresh the history (diabetes, new medications, smoking), assess reported hygiene compliance and objectify it with a plaque index.
Complete clinical examination. Probing at 4 to 6 sites per implant, assessment of bleeding and suppuration, verification of prosthetic stability (screw tightness, contact points, occlusal wear), and periodontal examination of the remaining dentition.
Supra- and submucosal debridement. Mechanical removal of biofilm and calcified deposits from all accessible surfaces, implants and teeth alike.
Targeted oral hygiene re-instruction. Chairside demonstration of calibrated interdental brushes, implant-specific floss, or single-tufted brushes according to prosthetic morphology.
Decision and scheduling. Record the data, compare against baseline values, and set the interval to the next visit according to the risk profile.
4.2Which instruments on titanium?
Historical dogma prohibited any metal instrument in contact with titanium and mandated plastic or carbon curettes. The current reading is more pragmatic. The priority objective is effective biofilm removal; plastic curettes, too flexible and too bulky, achieve this poorly in deep submucosal zones. Ultrasonic tips coated with PEEK or carbon, titanium curettes, and above all air polishing with glycine or erythritol powder delivered through a submucosal nozzle now offer the best compromise between decontamination efficacy and surface preservation. Air polishing with low-abrasivity powders has established itself as the instrument of choice for routine peri-implant maintenance: it removes biofilm from areas inaccessible to curettes, including exposed rough surfaces, without significant alteration of the titanium. Conventional sodium bicarbonate powder, considerably more abrasive, remains reserved for coronal surfaces.
Titanium curettes, sheathed ultrasonic tips. Effective on calcified deposits and calculus. Limited access to thread concavities and narrow subprosthetic areas. Remains indispensable where calculus is present.
Superior biofilm decontamination in deep sites and on rough surfaces, high patient comfort, no surface alteration. Ineffective against mineralised deposits. Caveat: very rare risk of submucosal emphysema; a purpose-designed nozzle is mandatory.
The superstructure of a screw-retained full-arch bridge blocks all access to the implant neck: debridement "around the prosthesis" in reality cleans only the ceramic.
Schedule periodic prosthesis removal — typically annually in the first year, then according to risk — allowing direct debridement of the abutments, verification of screw torque, and replacement of fatigued prosthetic screws. This retrievability must be anticipated at the design stage: favour screw-retained, recoverable assemblies, as argued in the DentoLink article on cement-retained versus screw-retained restorations.
Managing peri-implant mucositis
Mucositis is the decisive battleground: it is the only stage at which intervention is simple, inexpensive and fully reversible. Treatment rests on a tripod whose order of importance must be stated plainly. The first pillar, and by a wide margin the most decisive, is daily personal plaque control: no professional debridement compensates for deficient hygiene between visits. The second pillar is professional debridement following the protocol in section 4. The third pillar is correction of local factors: reshaping an over-contoured prosthetic profile, reopening embrasures, and removing residual excess cement — a classic iatrogenic cause of refractory mucositis around cement-retained restorations, which warrants meticulous exploration at the slightest doubt.
Regarding adjunctive antiseptics, the true state of the evidence should be stated honestly to the patient — and acknowledged to oneself: systematic reviews, including that of Jepsen and colleagues arising from the EFP workshop, conclude that adding chlorhexidine or other antiseptics to mechanical debridement yields no consistent, significant benefit over debridement alone in mucositis. A 0.12% chlorhexidine rinse may be considered as a short two-week adjunct in a markedly inflamed patient, but it never constitutes the treatment and should not be prolonged, given staining and dysgeusia. Complete resolution of mucositis is slow: bleeding on probing may persist for several weeks after plaque control has returned to an acceptable standard, and reassessment is reasonably scheduled at three months, not at eight days.
Mucositis is treated with an interdental brush and instruction, not with a prescription. Systemic antibiotics have no place in peri-implant mucositis, whatever its extent.
Managing peri-implantitis
6.1The stepwise logic of the 2023 EFP S3 guideline
The EFP S3-level clinical practice guideline published in 2023 (Herrera et al.) structures management into successive steps, mirroring stepwise periodontal therapy. The absolute prerequisite is control of risk factors: peri-implantitis treatment undertaken in a patient who smokes and whose plaque index exceeds 30% is destined to fail, and the guideline explicitly conditions progression to surgery on the achievement of satisfactory hygiene. The first therapeutic step is non-surgical treatment: complete submucosal debridement, over several visits if necessary, with reassessment at a minimum of six to eight weeks. Its limitations must be understood, however: unlike periodontitis, where non-surgical therapy resolves the majority of pockets, peri-implantitis responds favourably to debridement alone in only a minority of cases, since the macro- and micro-geometry of exposed threads makes complete blind decontamination mechanically impossible. Non-surgical therapy nevertheless retains full value: it reduces inflammation, tests patient compliance, and prepares the surgical field.
6.2Surgical treatment
When reassessment documents persistent deep pockets with bleeding or suppuration, a surgical step becomes necessary. Technique selection depends above all on bone defect morphology. Contained intrabony defects with three or four walls — the classic circumferential crater — are candidates for a reconstructive approach: access flap, meticulous decontamination of the implant surface, and grafting with a bone substitute with or without a membrane, following biological principles shared with guided bone regeneration, covered in the dedicated DentoLink article. Supracrestal or one-wall defects, particularly horizontal loss, fall under a resective approach: osteoplasty, apically repositioned flap and, where appropriate, implantoplasty — mechanical smoothing of exposed threads, converting a rough surface into a cleansable smooth one. Implantoplasty improves inflammatory control in non-regenerable zones but exposes the peri-implant mucosa to an aesthetic trade-off (recession, neck exposure) that must be disclosed to the patient before surgery, particularly in the anterior segment.
On intraoperative decontamination of the implant surface, scientific honesty compels the same observation made about antiseptics in mucositis: no protocol — titanium brushes, air polishing, laser, citric acid, saline — has demonstrated reproducible superiority over the others in comparative trials, and current guidance leaves the choice to the clinician while privileging mechanical rigour of access over sophistication of the chemical agent. Adjunctive systemic antibiotics are not recommended routinely: the inconsistent benefits reported do not offset antimicrobial resistance concerns, and their use is discussed case by case in severe, progressive forms, consistent with the rational prescribing principles set out in the DentoLink article on antibiotic therapy.
6.3Knowing when to explant
Bone loss exceeding half to two-thirds of implant length, mobility, implant fracture, or repeated treatment failures in a non-compliant patient should all prompt the indication for removal. Persisting with a doomed implant destroys bone capital that the replacement solution will sorely need. Removal by trephine or reverse-torque device is an act of treatment, not a personal failure.
6.4Algerian context
The organisation of implant follow-up in Algeria presents particularities the clinician must account for. A substantial proportion of implant patients were treated in another practice, sometimes abroad, and present without records: no baseline radiograph, unknown implant brand and connection — complicating both diagnosis (bone loss cannot be dated) and prosthetic management (drivers and retrieval components unobtainable). It is therefore prudent to systematise, for every new implant patient, an entry periapical radiograph that will serve as a new reference, and to issue the patient an implant passport recording brand, diameter, length and connection — a reflex that will protect the next colleague. Furthermore, availability of fine-powder air-polishing units remains uneven across facilities; in their absence, rigorous debridement with titanium curettes and sheathed ultrasonic tips remains an acceptable standard, the essential factor being regularity of follow-up. Chlorhexidine-based mouth rinses available on the national market cover the occasional indications described above, in short courses exclusively. Finally, since maintenance is generally not reimbursed under implant procedures, its cost should be stated in the initial treatment estimate so that follow-up is not abandoned for financial reasons — the leading avoidable cause of late peri-implantitis.
Risk factors and individualised recall intervals
7.1Hierarchy of risk factors
Not all implant patients carry the same risk, and the maintenance interval should reflect that heterogeneity. The most powerful and best-documented risk factor is a history of periodontitis: a patient treated for periodontitis, even when stable, retains a peri-implantitis risk several times that of a patient with a virgin periodontium, and that risk rises further if residual pockets persist on natural teeth at the time of implant placement. Next come poor maintenance compliance — the factor over which the clinician has the greatest leverage — smoking, and poorly controlled diabetes, whose perioperative management and periodontal impact are detailed in the DentoLink article on applied internal medicine. To these are added local prosthetic factors: residual cement, convex emergence profiles that close off access to interdental brushes, and absence of peri-implant keratinised mucosa which, without being a demonstrated causal factor for peri-implantitis, is associated with brushing discomfort and increased inflammation when its height falls below two millimetres.
Dominant factor. Complete periodontal stabilisation required before implant placement; close-interval maintenance for life.
Increased risk of peri-implantitis and poorer treatment response. Cessation to be built into the treatment plan.
Elevated HbA1c associated with heightened inflammatory risk. Coordinate with the treating physician.
Irregular follow-up multiplies peri-implantitis incidence. An active recall system is indispensable.
Residual cement, over-contouring, closed embrasures: iatrogenic factors correctable chairside.
Height below 2 mm: hygiene discomfort and increased inflammation; grafting to be discussed case by case.
7.2Setting the interval
No universal interval has been validated by randomised trials, and this should be acknowledged rather than papered over with a dogmatic figure. Consensus practice, consistent with cohort data from Monje and Roccuzzo, is never to exceed six months between visits in the most favourable implant patient, and to tighten to three or four months as soon as there is a history of periodontitis, smoking, diabetes, recurrent mucositis, or a complex prosthesis. The patient treated for peri-implantitis warrants three-monthly follow-up in the long term. The interval is not fixed: it is reassessed at every visit according to bleeding, plaque index and radiographic stability, following the same adaptive logic as supportive periodontal therapy.
Practical synthesis
Document the baseline: periapical radiograph and full probing chart at delivery of the definitive prosthesis, filed with the implant brand and connection.
Probe every implant at every visit, gently, at 4 to 6 sites: bleeding on probing is the earliest and most reliable alarm signal.
Diagnose by comparison with the patient's own baseline values, never on an isolated absolute probing depth.
Treat mucositis immediately and completely: personal hygiene, debridement, correction of prosthetic factors — without antibiotics and without long-term antiseptics.
Favour fine-powder air polishing for routine decontamination; reserve titanium curettes and sheathed ultrasonics for calcified deposits.
In peri-implantitis, do not linger on ineffective non-surgical therapy: reassess at 6–8 weeks and proceed to surgery matched to defect morphology.
Make any surgery conditional on prior control of hygiene and risk factors, smoking and diabetes foremost.
Set an individualised maintenance interval — 3 to 6 months — and reassess it at every visit; know when to explant a doomed implant to preserve bone capital.
8.1Frequently asked questions
Can an implant be probed with a conventional metal probe?
Yes. Gentle probing (around 0.25 N) with a metal periodontal probe is harmless to peri-implant tissues and to the implant surface. The historical requirement for plastic probes is no longer supported by current evidence.
Does a probing depth of 6 mm mean peri-implantitis?
Not on its own. A stable deep reading, without bleeding or progressive bone loss, may reflect a deeply placed implant that is entirely healthy. Diagnosis requires bleeding or suppuration together with documented progressive bone loss, or the 2017 consensus fallback criteria where no baseline exists.
Should antibiotics be prescribed in peri-implantitis?
Not routinely. The 2023 EFP S3 guideline does not endorse systematic adjunctive systemic antibiotics, since their inconsistent benefits do not justify the resistance risk. Their use is discussed case by case in severe, progressive forms, and never as monotherapy.
How often should an implant patient without risk factors be reviewed?
At most every six months. This tightens to three or four months in the presence of a periodontitis history, smoking, diabetes, recurrent mucositis, or after treatment of peri-implantitis.
What should be done for a patient implanted elsewhere with no records?
Establish a new baseline: entry periapical radiograph, full probing chart, photographs. Attempt to identify the connection (comparative radiography, identification platforms) before any disassembly. Then issue the patient an implant passport for the future.
References
- Berglundh T, Armitage G, et al. Peri-implant diseases and conditions: consensus report of workgroup 4 of the 2017 World Workshop. J Clin Periodontol. 2018.Consensus
- Herrera D, Berglundh T, Schwarz F, et al. Prevention and treatment of peri-implant diseases — the EFP S3 level clinical practice guideline. J Clin Periodontol. 2023.Guideline
- Derks J, Tomasi C. Peri-implant health and disease: a systematic review of current epidemiology. J Clin Periodontol. 2015.
- Costa FO, Takenaka-Martinez S, et al. Peri-implant disease in subjects with and without preventive maintenance: a 5-year follow-up. J Clin Periodontol. 2012.Cohort
- Jepsen S, Berglundh T, et al. Primary prevention of peri-implantitis: managing peri-implant mucositis. J Clin Periodontol. 2015.Consensus
- Renvert S, Persson GR, et al. Peri-implant health, peri-implant mucositis, and peri-implantitis: case definitions and diagnostic considerations. J Clin Periodontol. 2018.Consensus
- Schwarz F, Derks J, Monje A, Wang HL. Peri-implantitis. J Periodontol. 2018.Review
- Heitz-Mayfield LJA, Salvi GE. Peri-implant mucositis. J Clin Periodontol. 2018.Review
- Monje A, Aranda L, et al. Impact of maintenance therapy for the prevention of peri-implant diseases: systematic review and meta-analysis. J Dent Res. 2016.
- Roccuzzo M, De Angelis N, et al. Ten-year results of a three-arm prospective cohort study on implants in periodontally compromised patients. Clin Oral Implants Res. 2012.Cohort
- Salvi GE, Ramseier CA. Efficacy of patient-administered mechanical and/or chemical plaque control protocols in the management of peri-implant mucositis: a systematic review. J Clin Periodontol. 2015.
- Ramanauskaite A, Fretwurst T, Schwarz F. Efficacy of alternative or adjunctive measures to conventional non-surgical and surgical treatment of peri-implant mucositis and peri-implantitis: a systematic review. Int J Implant Dent. 2021.
- Lindhe J, Lang NP. Clinical Periodontology and Implant Dentistry. 6th edition, Wiley-Blackwell.Classic