
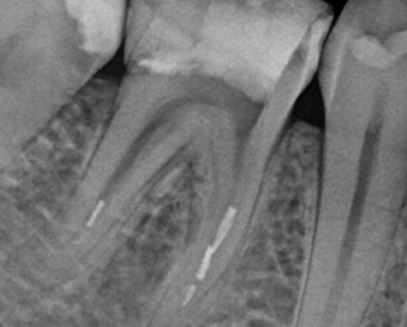
- Epidemiology and prognostic impact
- Biological impact: vital vs necrotic pulp
- Biomechanical aetiology of separation
- Metallurgical revolutions: heat treatments
- EDM: the manufacturing breakthrough
- Prevention protocols and biomechanics
- AAE clinical decision-making algorithm
- Advanced retrieval techniques
- Guided endodontics and dynamic navigation
- Bypassing: the elegance of conservation
Contemporary endodontics stands as one of the most demanding fields in dental medicine, requiring micrometric precision within a complex, often blind, three-dimensional anatomical environment. The advent and universal adoption of rotary and mechanised nickel-titanium (NiTi) instruments have indisputably revolutionised the discipline, optimising the biomechanical shaping of the canal system, improving preparation reproducibility, reducing operator fatigue, and preserving the original root canal anatomy far more effectively than traditional stainless steel instruments. However, this major technological leap has paradoxically intensified a dreaded iatrogenic complication: intracanal instrument fracture, commonly referred to as "instrument separation".
When an instrument fractures, every clinician — regardless of experience level — traverses an emotional spectrum ranging from frustration to distress, generating significant clinical anxiety. The presence of a metallic fragment obstructing the canal lumen impedes the fundamental procedures of debridement, chemical disinfection, and three-dimensional shaping, thereby compromising the overall efficacy of endodontic therapy. Today, the management of fractured instruments has transcended empiricism to become a highly scientific, protocol-driven endeavour.
Epidemiology, Risk Factors and Prognostic Impact
Understanding the true incidence of instrument fractures and their impact on long-term prognosis forms the foundation upon which all clinical decision-making rests. Contrary to common belief, NiTi instrument separation is not a rare event, though reported percentages vary considerably depending on study methodology, instrument types evaluated, and operator skill level.
Prevalence and Anatomical Distribution
Retrospective analyses and recent prospective studies indicate that the fracture rate for endodontic instruments generally ranges between 1.83% and 8.2%, depending on the cohort and instrumentation system used. A large-scale epidemiological study analysing the records of specialised endodontic practices covering 8,460 cases established an overall prevalence of retained fractured instruments at 3.3% of treated teeth. More recently, systematic reviews and meta-analyses including Trial Sequential Analysis (published 2024) evaluated successes and failures during endodontic retreatments involving separated instruments. Out of a cumulative cohort of 1,133 retreated teeth presenting with a fragment, the researchers recorded 172 retrieval failures (approximately 15.1%) and 55 iatrogenic perforations (approximately 4.8%).
| Fragment Location | Retrieval Failure Rate (2024 Meta-analysis) | Associated Risks |
|---|---|---|
| Coronal / Middle third | 8.8% | Moderate risk of tissue loss; direct access usually achievable |
| Apical third | 21.0% | Major perforation risk; canal trajectory alteration; severe root weakening |
| Overall perforation rate | ~4.8% - 6.5% | Periodontal damage; potential tooth loss if unmanageable |
Meta-analytic data unequivocally demonstrate that retrieval failures are significantly more frequent when instruments are lodged in the apical third (21% failure rate) compared to the middle or coronal third (8.8%). This disparity reflects the increasing anatomical complexity, the often pronounced curvature at this level, and the thinning of dentinal walls, making direct access via retrieval instruments extremely hazardous without risking perforation or fatal structural weakening of the root.
Biological Impact: The Vital vs Necrotic Distinction
One of the most important conceptual advances in modern endodontics has been the demystification of the biological role of the metallic fragment. It has been formally established that a fractured instrument, whether stainless steel or NiTi alloy, is an inert, biocompatible material. The fragment itself induces no inflammatory tissue response, triggers no immune rejection reaction, and is not responsible for the development of periapical lesions. The true culprit behind endodontic failure, the appearance or exacerbation of a rarefying osteitis (periapical lesion), is exclusively the intraradicular infection — specifically, the persistence of a complex bacterial biofilm beyond the metallic obstruction.
The metallic fragment itself causes periapical pathology and mandates extraction in all cases, irrespective of the pulpal status or stage of canal preparation at the time of fracture.
A case-control study of 146 teeth with retained instruments vs 146 matched controls demonstrated healing rates of 91.8% and 94.5% respectively — a difference that did not reach statistical significance (p > 0.05). The fragment is biologically inert; it is the bacterial load apical to the obstruction that dictates the prognosis.
A systematic review concluded that prognosis is not significantly reduced if apical pathology is absent at the time of fracture (e.g. biopulpectomy for irreversible pulpitis). Conversely, if disease is present (necrosis, apical periodontitis), healing is significantly compromised.
Biomechanical Aetiology of Instrument Separation
Understanding the physical mechanisms leading to NiTi alloy rupture is essential for implementing effective prevention strategies. The aetiology is multifactorial, involving the intrinsic complexity of the canal anatomy, the mechanical properties of the file system, sterilisation protocols, and above all, the dynamics of clinical instrumentation. NiTi file failures are universally classified into two distinct biomechanical phenomena that may act independently or, more commonly, synergistically.
Metallurgical Revolutions: Heat Treatments and Alloy Engineering
In response to the fracture susceptibility of NiTi, the endodontic industry has delivered a decade of uninterrupted metallurgical innovation aimed at modifying the crystallographic structure of the alloy to optimise flexibility and fracture resistance. The NiTi alloy (approximately 56% nickel, 44% titanium by weight) possesses the unique property of transitioning between two distinct crystalline phases depending on thermal or mechanical stress: the austenitic phase and the martensitic phase.
Cubic crystal structure present at high temperature. Rigid, hard, and confers shape memory — the tendency to spring back to the original straight form. First-generation instruments operated entirely in this phase at body temperature.
Monoclinic crystal structure appearing at lower temperature or under stress. Flexible, ductile, and allows reversible plastic deformation, absorbing energy without fracturing. The key innovation has been to shift the austenite finish temperature (Af) above body temperature (~37 degrees C) so instruments operate in this phase in vivo.
The Evolution of Thermally Treated Alloys
| Metallurgical Technology | Clinical Examples | Af Temperature (approx.) | Characteristics and Clinical Recommendations |
|---|---|---|---|
| Conventional NiTi | ProTaper Universal, ProFile | < 20 degrees C (Austenitic) | High buckling resistance, aggressive cutting. Recommended for straight canals or retreatment cases. |
| M-Wire | ProTaper Next, WaveOne | ~35-45 degrees C | First-generation heat-treated alloy. Pre-manufacturing treatment integrates martensitic structures and R-phase. Significantly improved flexibility over conventional NiTi. |
| CM-Wire | HyFlex CM | > 50 degrees C | Controlled Memory wire. Shape memory almost entirely suppressed at room temperature. Files can be manually bent and retain their shape. Drastically reduces straightening forces on curved canal walls. |
| Blue Wire | Reciproc Blue, Vortex Blue | 33-38 degrees C | Surface oxide layer 60-80 nm. Extreme flexibility. Ideal for abrupt curvatures. Risk of unwinding in highly constricted canals. |
| Gold Wire | WaveOne Gold, ProTaper Gold | 47-51 degrees C (Martensitic) | Oxide layer 100-140 nm. Strongly martensitic in vivo. Optimal balance between cyclic fatigue resistance and torsional resistance. Ideal for universal use and narrow canals. |
| EDM (Electrical Discharge Machining) | HyFlex EDM | > 50 degrees C (Strongly Martensitic) | Surface free of machining defects. Ultimate cyclic fatigue resistance at body temperature. The alloy of choice for extremely tortuous anatomies. |
| DualWire / MaxWire | BlueShaper PRO, XP-3D | Variable by section | Adaptive phase change. DualWire combines a Gold apical third (resistant) and a Blue shaft (flexible). Represents the latest generation of variable-property instruments. |
EDM: The Manufacturing Breakthrough
While heat treatments improve the alloy itself, the traditional abrasive milling manufacturing method inevitably creates micro-scratches and surface defects that act as stress concentrators, initiating cyclic fatigue. Electrical Discharge Machining (EDM), integrated notably in the HyFlex EDM system, has revolutionised file fabrication.
EDM uses high-frequency electrical discharges under a dielectric fluid to locally melt and evaporate the nickel-titanium with zero physical contact. This process creates a unique cratered surface entirely devoid of the milling lines inherent to conventional manufacturing. Laboratory trials consistently demonstrate that EDM instruments exhibit the highest cyclic fatigue resistance, surpassing both Gold and Blue alloys, particularly at the critical body temperature of 37 degrees C. This makes EDM the alloy of choice for extremely tortuous canal anatomies.
Prevention Protocols and Biomechanical Preparation
Despite these metallurgical advances, fracture prevention rests primarily on clinical expertise and strict adherence to biomechanical preparation protocols. The scientific literature highlights the vital importance of several preparatory steps designed to reduce stress on rotary instruments.
Coronal Preflaring
Coronal preflaring is an indispensable prophylactic procedure. The natural anatomy of the pulp chamber and the cervical third of the root often presents dentinal triangles and interferences that force the instrument to bend from the moment it enters the canal. By removing these overhangs, the clinician establishes straight-line access to the apical third. The biomechanical impact is substantial: coronal preflaring reduces the effective angle of curvature that the instrument must negotiate in the middle or apical third. In vitro studies have confirmed that this step significantly extends the cyclic lifespan of rotary instruments before fracture. Clinically, cervical preparation also facilitates irrigant penetration and has been associated with a significant reduction in postoperative pain.
Glide Path Establishment
Establishing a glide path is defined as creating a smooth, reproducible, continuous tunnel extending from the canal orifice to the apical constriction. It is the absolute foundation of mechanised endodontics. The aim is to ensure that the canal is free of obstructions and that the initial canal diameter is at least equivalent to that of the tip of the first NiTi rotary file.
Kinematics: Reciprocation vs Continuous Rotation
Reciprocating single-file systems have gained immense popularity for their efficiency and simplicity. The reciprocating kinematics function through alternating cutting and release movements (back-and-forth rotations with unequal angles). This non-continuous motion acts as a biological shield against fracture: when the blade engages in dentine, the cutting angle is immediately followed by a reverse release angle, disengaging the flutes before the alloy's elastic limit is reached. Multiple comparative studies invariably conclude that files operating in reciprocating motion exhibit significantly superior cyclic fatigue and torsional resistance compared to files of the same design operating in continuous rotation.
The AAE Clinical Decision-Making Algorithm: Retrieve, Bypass, or Entomb?
When prevention fails and fracture occurs, the clinician faces a dilemma that must be resolved not through emotion or dogged persistence, but through rigorous application of an evidence-based decision-making algorithm. The American Association of Endodontists (AAE), through the work of Dr Michael Solomonov, has proposed a comprehensive clinical algorithm. Its cardinal principle: "Primum non nocere" — first, do no harm.
The Solomonov algorithm stratifies management protocols according to two fundamental clinical parameters: pulpal infectious status (vitality vs necrosis/infection) and anatomical position of the fragment within the root (apical, middle, or coronal third).
Scenario 1 — Vital Pulp (Non-infected or Minimally Infected Canal)
Scenario 2 — Non-Vital Pulp (Infected Case)
In cases of pulp necrosis, typically accompanied by periapical lesions, the decision is intrinsically linked to the stage of cleaning and shaping at the precise moment of fracture.
| Pulpal Status & Stage | Fragment Location | Recommended Strategy (AAE Algorithm) | Risks and Follow-up |
|---|---|---|---|
| Vital | Apical | Do not retrieve. Obturate to fragment. | Low biological risk. High biomechanical risk if retrieval attempted. |
| Vital | Middle | Attempt bypass. If fail, obturate to fragment. | Mandatory follow-up. Apical surgery if subsequent failure. |
| Vital | Coronal | Active retrieval. | Strict dentine preservation required. |
| Non-vital / After shaping to #30 | Apical | Do not retrieve. Obturate to fragment. | Strict clinical follow-up. Apical surgery frequent if lesion stagnates. |
| Non-vital / After shaping to #30 | Middle | Attempt bypass. If fail, obturate to fragment. | Same prognosis as vital case once bacterial load is reduced. |
| Non-vital / Before shaping | Any | Aggressive bypass or retrieval. Surgery if orthograde access fails. | High failure risk if obstruction cannot be overcome. |
A 2025 systematic review and meta-analysis reported a pooled Odds Ratio of 20.39 in favour of successful active management (bypass or retrieval). Endodontic therapy success rates jumped from 68.1% (with obstructing instrument) to 95% (after regaining apical access).
Advanced Retrieval Techniques
Once the decision to retrieve has been made, the practitioner must deploy a sophisticated technological arsenal. Any retrieval attempt without prior use of a dental operating microscope (DOM) is considered obsolete in modern endodontics, as the DOM provides the coaxial illumination and magnification (typically 10x to 16x) indispensable for locating and operating on micrometric structures.
1. Creating the Staging Platform
The orthograde surgical procedure invariably begins with establishing straight-line access and creating a staging platform at the coronal aspect of the fractured instrument. This step aims to expose the head of the fragment to permit insertion of grasping or activation instruments.
Modified Gates-Glidden (GG) drills (with the head decapitated to maximise the apical cutting diameter) or specialised micro-trephines are used. For example, the Terauchi protocol uses a modified GG #3 drill operating at 1,000 rpm clockwise to flare the access, followed by a micro-trephine (TFRK-MT, 0.7 mm diameter) operating at 600 rpm in counterclockwise rotation. The counterclockwise rotation is critical: if the trephine blades contact the instrument's flutes (which are typically right-hand threaded), the frictional energy will tend to unscrew the fragment upward. The goal is to clear a 180-degree semi-circular recess around the inner aspect of the curvature, exposing the fragment by 1 to 2 mm.
2. Ultrasonic Dynamics
Piezoelectric ultrasonic generators fitted with specific diamond-coated or smooth inserts (such as ProUltra inserts or EMS RT3 tips) constitute the gold standard for fragment dislodgement, particularly in the coronal and middle thirds. The ultrasonic insert (generating frequencies in the range of 24-33 kHz) is introduced into the space created during staging.
3. Micro-Mechanical Extraction Systems: TFRK and BTR-Pen
Ultrasonics have intrinsic limitations: they sacrifice dentine aggressively and can cause secondary insert fracture or further fragment fragmentation if power is too high. To address these drawbacks, dental engineering has developed sophisticated extraction kits.
Developed by Dr Yoshi Terauchi to standardise and rationalise retrieval with enhanced clinical predictability. The kit methodically groups preparation instruments (modified GG #3, micro-trephines), specific ultra-fine ultrasonic inserts (ED87, ED88, ED89), and the system's hallmark innovation: the Yoshi Loop (Endo File Remover, TFRK-L). This is a cannula containing an adjustable metallic micro-loop. If the fragment is long (greater than 4.5 mm) or does not yield after 10 seconds of well-conducted ultrasonic activation, the loop is slipped around the fragment head, tightened by pulling the handle latch, and a gentle coronal traction extracts the file. Overall success rate: ~95%.
A pen-shaped device with active tips housing an ultra-fine NiTi loop (0.3 mm diameter). The NiTi superelasticity allows the loop to curve and adapt to canal anatomy without permanent deformation. In vitro evaluations demonstrate that the BTR-Pen induces significantly less dentine loss than pure ultrasonic approaches or traditional tubular systems (e.g. Endo Rescue). Success rate: ~60% in indicated cases, particularly effective in the middle third where complex anatomy discourages prolonged ultrasonic use.
4. The Braiding Technique
For deeply located fragments (apical third) where ultrasonics or loops present unacceptable perforation risk, the braiding technique offers a non-surgical, extremely dentine-conservative alternative relying on an ingenious mechanical interlock.
Although dependent on fine tactile sensitivity, this technique is valued for its ability to preserve root architecture and is particularly useful when microscopic access to the fragment head is limited.
Guided Endodontics and Dynamic Navigation
The digital era has propelled endodontics toward new horizons of precision, particularly for resolving cases previously deemed inoperable via orthograde access — such as retrieval of fragments situated beyond severe curvatures or within obliterated, calcified canals.
Static Navigation (3D-Printed Guides)
The static guided endodontics workflow draws directly from modern implantology. It begins with a CBCT acquisition combined with an optical surface impression (STL file). Both datasets are superimposed in treatment planning software (e.g. BlueSkyBio). The practitioner virtually designs a perfectly rectilinear drilling vector targeting the fragment head at the heart of the root with millimetric precision, calculating the safest trajectory through the dentine.
A resin 3D-printed surgical guide incorporating a metallic guidance sleeve is then fabricated. In the clinical setting, the guide is positioned on the adjacent teeth, and a specific-diameter rotary micro-trephine is inserted through the sleeve. The guide imposes absolute rigidity on the drill, preventing any deviation or creation of false canals. Once drilling reaches the planned depth, the fragment tip is exposed, enabling straightforward extraction using ultrasonics or micro-extractors. Static navigation avoids the unnecessary dentine loss associated with "blind" searches under the microscope, massively increasing operative safety.
Dynamic Navigation in Real Time
Dynamic Navigation Systems (DNS) represent the cutting edge of this evolution. Dispensing with the delay and physical encumbrance of a printed guide (often difficult to seat in posterior molar sectors due to limited mouth opening), dynamic navigation relies on optical stereophotogrammetry.
Stereoscopic cameras track in real time optical markers fixed to the patient's jaw and to the dentist's handpiece. The computer screen superimposes the virtual position of the moving drill directly onto the pre-registered CBCT slices.
Bypassing: The Elegance of Conservation
It is imperative to recall that, per the AAE decision-making algorithm, retrieval is not the exclusive holy grail of fracture management. Bypassing stands as the most elegant and biologically sound option when physical extraction threatens root integrity, particularly when the fragment is sequestered beyond the major inflection of the curvature in the apical third.
Success rate approximately 75% under favourable conditions, but requires significant dentine sacrifice and carries thermal and perforation risks.
Overall success rate of 66.7%, climbing to 95% (OR = 20.39) when complete apical cleaning is achieved. Avoids massive dentine loss, preserves root architecture, and guarantees long-term functional tooth survival.
Frequently Asked Questions
Conclusion. The fracture of a nickel-titanium instrument during endodontic therapy, while anxiety-provoking, no longer constitutes the inevitable end of treatment nor a death sentence for the tooth. Contemporary scientific literature demonstrates that the discipline has achieved exceptional maturity in understanding and managing this iatrogenic incident.
The colossal advances in metallurgy — from austenitic alloys to highly martensitic heat-treated wires (Gold, Blue) and the integration of breakthrough EDM manufacturing technology — have drastically pushed back the limits of cyclic fatigue and torsional resistance. Yet these optimised mechanical properties cannot substitute for the inviolable respect of fundamental protocols: systematic coronal preflaring and glide path establishment remain the life insurance of every rotary or reciprocating instrument engaged within the canal network.
When separation occurs, the era of empirical persistence is over. Strict application of clinical decision-making algorithms — grounded in the delicate balance between the biological necessity of disinfection (dependent on pulpal vitality and apical periodontitis) and the biomechanical imperative of pericervical dentine preservation (to prevent VRF) — must guide the endodontist's judgement. The adage "Primum non nocere" governs the decision to entomb, bypass, or retrieve.
The therapeutic arsenal deployed today — operative microscopy, controlled ultrasonic dynamics, highly sophisticated micro-extraction kits (TFRK, BTR-Pen), and the spectacular integration of guided endodontics through static or dynamic navigation — delivers solutions with micrometric surgical precision. Mastery of these tools demands a rigorous learning curve, but guarantees unprecedented clinical predictability, enabling both the informed general practitioner and the specialist to overcome this mechanical obstacle, restore the radicular ecosystem, and ensure the lasting functional preservation of the tooth within the oral cavity.
References
1. Semantic Scholar — Instrumental fracture in endodontics: a short review. pdfs.semanticscholar.org
2. PMC — Cyclic fatigue resistance, torsional resistance, and metallurgical characteristics of M3 Rotary and M3 Pro Gold NiTi files. pmc.ncbi.nlm.nih.gov
3. PMC — Glide Path in Endodontics: A Literature Review of Current Knowledge. pmc.ncbi.nlm.nih.gov
4. AAE — Broken Instruments: Clinical Decision Making Algorithm. American Association of Endodontists. aae.org
5. ResearchGate — Management of Fractured Endodontic Instruments: A Clinical Guide. researchgate.net
6. PMC — Expert consensus on management of instrument separation in root canals. pmc.ncbi.nlm.nih.gov
7. MDPI / ResearchGate / PubMed — Analysis of Endodontic Successes and Failures in the Removal of Fractured Endodontic Instruments during Retreatment: A Systematic Review, Meta-Analysis, and Trial Sequential Analysis (2024). mdpi.com
8. PubMed — The impact of instrument fracture on outcome of endodontic treatment. pubmed.ncbi.nlm.nih.gov
9. RSD Journal — Removal of fractured instruments in root canals: Challenges, strategies, and clinical perspectives. rsdjournal.org
10. PubMed — Impact of a retained instrument on treatment outcome: a systematic review and meta-analysis. pubmed.ncbi.nlm.nih.gov
11. PubMed — The impact of fractured endodontic instruments on treatment outcome. pubmed.ncbi.nlm.nih.gov
12. PubMed — Endodontic instrument fracture: causes and prevention. pubmed.ncbi.nlm.nih.gov
13. Thieme — Impact of a Retained Instrument on Treatment Outcome: A Systematic Review. thieme-connect.com
14. PMC — Cyclic and Torsional Fatigue Resistance of Seven Rotary Systems. pmc.ncbi.nlm.nih.gov
15. ResearchGate — Instrument separation in endodontics: A review of risk factors and insights into underlying challenges. researchgate.net
16. Compendium — A Clinical Perspective on the Role of a Glide Path and the Use of Reciprocating Single Files Without Establishing One. compendiumlive.com
17. AAE — Trends in Rotary File Design. American Association of Endodontists. aae.org
18. PMC — Rotary science and its impact on instrument separation: A focused review. pmc.ncbi.nlm.nih.gov
19. ESMED — Cyclic Fatigue Resistance of Logic 25.06 Rotary Instruments. European Society of Medicine. esmed.org
20. PMC — Root Canal Instrumentation: Current Trends and Future Perspectives. pmc.ncbi.nlm.nih.gov
21. JOMDI — Comparison of cyclic fatigue resistance of different rotational and reciprocal file systems. jomdi.org
22. PMC — Experimental Analysis of the Influence of Heat Treatments on the Flexibility of NiTi Alloy for Endodontic Instruments Manufacturing. pmc.ncbi.nlm.nih.gov
23. PMC — Comparison of cyclic fatigue resistance of three different single-file systems. pmc.ncbi.nlm.nih.gov
24. MDPI — Mechanical Properties of NiTi Rotary Files Fabricated through Gold-Wire, CM-Wire, T-Wire, and R-Phase Heat Treatment. mdpi.com
25. IJCE — NiTi rotary system in endodontics: An overview. IP Indian J Conserv Endod. ijce.in
26. PMC — Bending resistance and cyclic fatigue resistance of WaveOne Gold, Reciproc Blue, and HyFlex EDM instruments. pmc.ncbi.nlm.nih.gov
27. JournalAgent — Comparison of the Fracture Resistance of HyFlex EDM and WaveOne Gold Rotary System Instruments in Abrupt Apical Curvature. pdf.journalagent.com
28. MDPI — Comparative Analysis of Nickel-Titanium Instrumentation Systems for Root Canal Anatomy Preservation: An In Vitro Study. mdpi.com
29. RDE — Effect of quality of radiographs taken during root canal treatment on technical quality of root canal fillings and endodontic outcome. rde.ac
30. PMC — Investigation of the effect of low torque and speed values on postoperative pain after root canal treatment: a randomised clinical trial. pmc.ncbi.nlm.nih.gov
31. ResearchGate — Glide Path: An Ineluctable Route for Successful Endodontic Mechanics: A Literature Review. researchgate.net
32. Medical Journal International — The Analysis Study of Resistance to Cyclic Fatigue in Rotary versus Reciprocating Endodontic Instruments. medicaljournalinternational.org
33. AAE — Flowcharting of the Proposed Clinical Decision-Making Algorithm of Broken Endodontic Instruments: Decision-making to Retrieve, Bypass, or Entomb (Solomonov). aae.org
34. ResearchGate — Success Outcomes for Bypass or Retrieval of Fractured Endodontic Instruments: A Systematic Review (2025). researchgate.net
35. PMC — Non-surgical Retrieval of Separated Endodontic Files Using Ultrasonic Techniques. pmc.ncbi.nlm.nih.gov
36. PMC — Novel electromagnetic device to retrieve fractured stainless steel endodontic files: an in-vitro investigation. pmc.ncbi.nlm.nih.gov
37. Dental Tribune US — Removing separated files with the Terauchi File Retrieval Kit. us.dental-tribune.com
38. Osada — Terauchi File Removal Kit Instruction Manual. osada.co.il
39. SoniDent — DTE Dr. Terauchi Broken File Removal Tips. sonident.ca
40. PMC — The Efficiency of the BTR-Pen System in Removing Different Types of Separated Instruments. pmc.ncbi.nlm.nih.gov
41. ResearchGate — Degradation of separated instruments with or without static navigation versus ultrasonic retrieval (An In-Vitro study). researchgate.net
42. Physics Forceps — TFRK: Terauchi File Retrieval Kit. physicsforceps.com
43. JCHR — Analyzing the Effectiveness of Different Methods for Instrument Retrieval: A Comprehensive Systematic Review. jchr.org
44. PMC / PubMed — Comparative evaluation of the effectiveness of ultrasonic tips versus the Terauchi file retrieval kit for the removal of separated endodontic instruments. pmc.ncbi.nlm.nih.gov
45. BTR-Pen — Broken Tool Removal System (manufacturer). btr-pen.com
46. ResearchGate — Comparative Evaluation of Different Techniques and Devices for Removal of Intra Canal Separated Instruments with Different Lengths (In Vitro). researchgate.net
47. PMC — Comparative Evaluation of the Efficiency in Retrieving Separated Reciprocating Instruments Using Three Different File Retrieval Systems in Maxillary First Molars: An In Vitro Study. pmc.ncbi.nlm.nih.gov
48. RDE — Predictive factors in the retrieval of endodontic instruments: the relationship between the fragment length and location. rde.ac
49. PMC — An Innovative Approach for Retrieval of a Separated Intracanal File Using Guided Endodontics: A Case Report. pmc.ncbi.nlm.nih.gov
50. JCDP — Guided Endodontics in the Management of Intracanal Separated Instruments: A Case Report. thejcdp.com
51. ResearchGate — Instrument retrieval using ultrasonics and minimally invasive guided endodontics using AReneto system: a case report. researchgate.net
52. PMC — Dynamic Navigation in Endodontic Surgery: A Systematic Review (2025). pmc.ncbi.nlm.nih.gov
53. PMC — Factors Affecting the Success of Endodontic Instrument Fragment Retrieval: An Impact of Anatomical and Clinical Variables. pmc.ncbi.nlm.nih.gov
54. Gold Coast Dental — Non-Surgical Endodontic Retreatment: 2026 Clinical Guide. goldcoastdental.com